Below is the complete SEO-focused article, written without references or citations and with the requested medical context and reader-friendly tone.
BUN Creatinine Ratio: Normal Range & What It Means
The BUN creatinine ratio is a commonly reviewed measurement on blood tests that can provide useful information about hydration, kidney function, protein metabolism, and several other processes in the body. It compares blood urea nitrogen, commonly called BUN, with the amount of creatinine circulating in your blood. Doctors generally interpret the ratio alongside the individual BUN and creatinine values rather than treating it as a diagnosis by itself. A result outside the expected range can occur for many reasons, including dehydration, dietary factors, gastrointestinal bleeding, changes in muscle mass, liver problems, and kidney-related conditions. Understanding what the numbers represent can make a laboratory report much less confusing. However, the meaning of any abnormal result depends heavily on your symptoms, medical history, medications, and other laboratory findings.
What Is the BUN Creatinine Ratio?
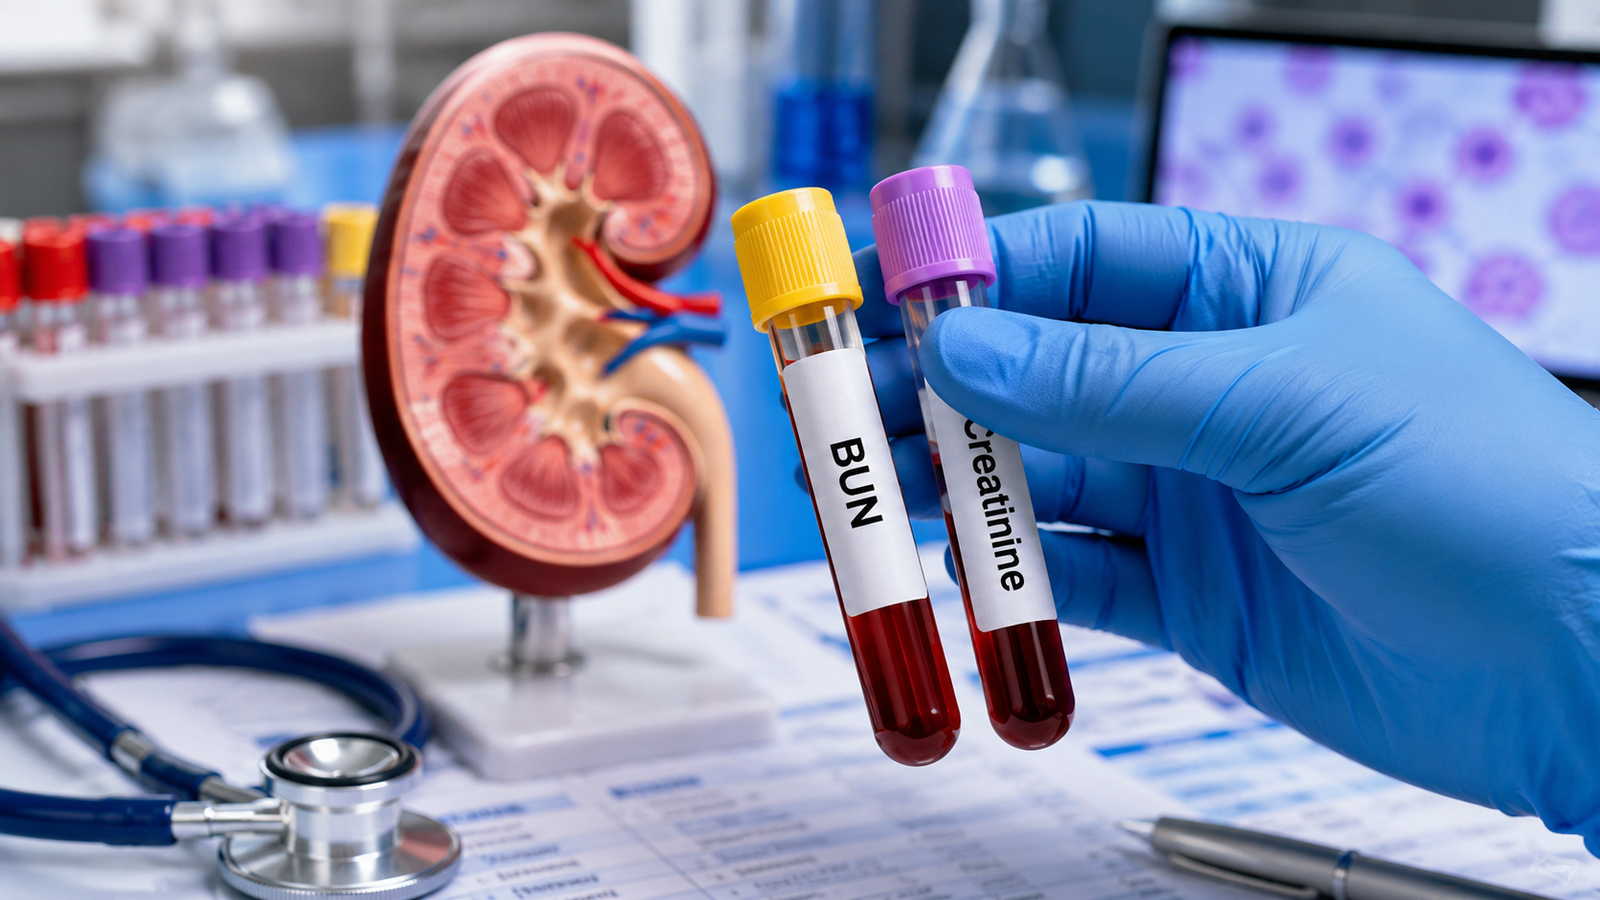
The BUN creatinine ratio compares two waste-related substances measured through a blood test: blood urea nitrogen and creatinine. Blood urea nitrogen measures the amount of nitrogen in the blood that comes from urea, a waste product created when the body processes protein. The liver produces urea, and the kidneys normally remove much of it through urine. Creatinine, meanwhile, is produced largely from the normal activity and metabolism of muscles. The kidneys also filter creatinine from the bloodstream, which makes its blood concentration useful when evaluating kidney filtration. By comparing these two measurements, clinicians can sometimes gain additional clues about why one or both values are abnormal.
BUN and creatinine do not behave exactly the same way in the body, which is why calculating their relationship can occasionally provide useful information. BUN can change because of kidney function, hydration, protein intake, gastrointestinal bleeding, liver function, and increased protein breakdown. Creatinine is generally influenced more strongly by kidney filtration, muscle mass, age, medications, and certain forms of muscle injury. Because different factors affect each measurement, one value may rise more dramatically than the other. The resulting ratio can therefore help clinicians consider whether dehydration, altered blood flow to the kidneys, kidney disease, or another process might be contributing. Even so, the ratio should never be interpreted without considering the actual BUN and creatinine numbers.
The calculation itself is relatively simple when both measurements are reported in milligrams per deciliter. The BUN value is divided by the creatinine value to produce the ratio. For example, a BUN level of 18 mg/dL with a creatinine level of 1.0 mg/dL produces a BUN creatinine ratio of 18:1. Laboratories may automatically calculate and display this number on metabolic panels, while others report only BUN and creatinine. Importantly, calculations using different measurement units may not correspond to the commonly discussed ratio ranges. This is one reason people should compare their results with the reference interval printed directly on their laboratory report rather than relying only on online charts.
A BUN creatinine ratio is usually available as part of routine blood testing rather than being ordered as an isolated laboratory test. BUN and creatinine frequently appear on a basic metabolic panel or comprehensive metabolic panel, both of which provide additional information about metabolic and kidney-related health. These panels can also measure substances such as sodium, potassium, glucose, bicarbonate, and calcium. A healthcare professional may order them during routine health screening, before certain medical procedures, when someone is taking particular medications, or when kidney problems are suspected. Because the test is widely available and inexpensive, it is commonly used as one component of broader clinical evaluation.
It is important to understand that the BUN creatinine ratio is a clue rather than a final answer. A high ratio does not automatically mean kidney failure, and a low ratio does not necessarily indicate serious disease. Temporary factors such as dehydration, dietary changes, strenuous exercise, illness, or medications can influence blood results. Doctors usually look for patterns across several tests and sometimes repeat laboratory testing before reaching conclusions. Kidney assessment may also involve estimated glomerular filtration rate, urine testing, electrolyte levels, blood pressure, and imaging depending on the situation. Interpreting all these findings together provides a more meaningful picture than focusing on a single laboratory number.
What Is a Normal BUN Creatinine Ratio?
A commonly used normal BUN creatinine ratio in adults is approximately 10:1 to 20:1 when BUN and creatinine are both measured in mg/dL. However, this range should be treated as a general guide rather than a universal rule. Individual laboratories can use slightly different reference intervals based on their testing methods, populations, and reporting standards. Some healthy people may therefore have a ratio just outside this range without having a significant medical problem. The individual values of BUN and creatinine are often more clinically important than the ratio itself. For the most accurate interpretation, always compare your result with the reference range shown next to it on your own laboratory report.
A normal ratio generally suggests that BUN and creatinine are present in a proportion commonly seen when protein metabolism, hydration, and kidney filtration are reasonably balanced. However, a normal ratio does not guarantee that both individual values are normal. BUN and creatinine can sometimes rise together while maintaining an apparently normal ratio. For example, certain people with impaired kidney filtration may have elevated levels of both substances without producing a dramatically abnormal ratio. Conversely, both values could be relatively low while the mathematical relationship between them remains normal. This is why clinicians examine the complete laboratory panel rather than checking whether the ratio simply falls between two numbers.
Normal BUN values vary somewhat between laboratories, age groups, and clinical circumstances. Similarly, creatinine reference ranges differ depending on factors such as muscle mass, age, biological sex, and laboratory methods. A muscular person may naturally have a somewhat higher creatinine level than someone with much less muscle tissue. Older adults with low muscle mass can sometimes have deceptively low creatinine levels even when kidney filtration is reduced. Dietary protein can also influence BUN, especially after substantial changes in protein consumption. These variables explain why there is no single ideal BUN creatinine ratio that applies perfectly to every person.
Hydration status can produce noticeable changes even when the kidneys themselves are functioning normally. When the body is short on fluid, the kidneys conserve water and the concentration of certain substances in the blood can increase. BUN often rises more noticeably than creatinine during reduced blood flow related to dehydration, potentially increasing the ratio. After hydration is restored, the values may move back toward the individual’s usual range. This is one reason clinicians may ask whether someone experienced vomiting, diarrhea, fever, heavy sweating, or poor fluid intake before blood testing. A single mildly abnormal result therefore needs context before it can be considered medically significant.
Trends over time are often more valuable than one isolated measurement. Someone whose BUN, creatinine, estimated glomerular filtration rate, and electrolytes have remained stable over several years may be interpreted differently from someone whose kidney-related numbers changed suddenly. Doctors often compare new laboratory results with previous blood tests to determine whether an abnormality is temporary, persistent, or progressively worsening. A repeat test may be recommended when dehydration, illness, medication effects, or laboratory variation could have influenced the first result. Persistent abnormalities usually deserve further investigation, particularly when accompanied by symptoms or other kidney-related findings. The ratio is most informative when viewed as one part of that larger pattern.
What Does a High BUN Creatinine Ratio Mean?
A high BUN creatinine ratio generally means that the BUN level has increased disproportionately compared with creatinine. Dehydration is one of the most common situations associated with this pattern because reduced circulating blood volume can increase urea reabsorption in the kidneys. Someone who has had persistent vomiting, diarrhea, fever, heavy sweating, or inadequate fluid intake may therefore develop an elevated ratio. Reduced blood flow to the kidneys from other causes can produce a similar pattern. However, the ratio alone cannot determine whether dehydration is present or identify its severity. Symptoms, physical examination findings, blood pressure, electrolytes, urine output, and other laboratory results help provide a more complete explanation.
Reduced blood flow to the kidneys is sometimes described clinically as a prerenal cause of abnormal kidney-related laboratory results. It can occur with significant dehydration, blood loss, low blood pressure, or conditions that reduce effective circulation. Under these circumstances, the kidneys may still be structurally capable of filtering blood but receive less blood than they normally require. BUN can rise disproportionately because more urea is reabsorbed as the kidneys conserve fluid. Creatinine may also increase if reduced kidney perfusion becomes substantial or persistent. Identifying and correcting the underlying cause is important because prolonged reductions in kidney blood flow can eventually contribute to actual kidney injury.
Gastrointestinal bleeding, particularly bleeding higher in the digestive tract, can also produce an elevated BUN relative to creatinine. Blood entering the stomach or intestine is digested as a protein source, which can increase the amount of urea produced by the liver. As a result, BUN may rise more strongly than creatinine and increase the ratio. Possible signs of gastrointestinal bleeding include black, tar-like stools, vomiting blood, dizziness, weakness, fainting, or symptoms of anemia. These symptoms require prompt medical evaluation rather than interpretation through laboratory values alone. An elevated BUN creatinine ratio may support clinical suspicion, but it cannot confirm where bleeding is occurring.
Protein metabolism can influence the ratio as well. A substantial increase in dietary protein may raise BUN because breaking down protein produces nitrogen-containing waste that ultimately becomes urea. Increased tissue breakdown associated with severe illness, fever, trauma, or other catabolic conditions may have a similar effect. Certain medications, including corticosteroids in some circumstances, can also influence protein metabolism and BUN levels. These factors may increase the ratio without indicating a primary kidney disorder. Healthcare professionals therefore often ask about diet, supplements, recent illnesses, medications, and changes in physical condition when evaluating an unexpectedly high result.
A high ratio should not automatically be interpreted as kidney disease or kidney failure. Kidney disorders can certainly affect BUN and creatinine, but many kidney conditions raise both measurements rather than creating a dramatically disproportionate increase in BUN. The pattern becomes more meaningful when combined with the creatinine level, estimated glomerular filtration rate, electrolytes, urinalysis, symptoms, and clinical history. A mildly elevated ratio in someone who recently exercised heavily or became dehydrated is very different from rapidly worsening kidney numbers in someone who is acutely ill. Persistent or substantial abnormalities deserve medical evaluation. The goal is always to identify the underlying process rather than treating the ratio itself.
What Does a Low BUN Creatinine Ratio Mean?
A low BUN creatinine ratio means that BUN is relatively low compared with creatinine. This pattern can develop because BUN decreases, creatinine increases, or both changes happen at the same time. Low protein intake is one possible reason because the body produces urea when it breaks down dietary and body proteins. Someone consuming very little protein may consequently produce less urea, resulting in a lower BUN measurement. This does not necessarily mean there is a disease, especially if other laboratory values and overall health are normal. Nevertheless, unexpectedly low results should be considered alongside nutritional status, recent dietary changes, liver function, hydration, muscle health, and kidney filtration.
Because the liver is responsible for producing urea, significant impairment of liver function can sometimes lower BUN. In this situation, reduced urea production may decrease the numerator of the BUN creatinine ratio and create a lower-than-expected result. A low ratio by itself is not sufficient to diagnose liver disease, however. Liver problems are usually assessed using symptoms, medical history, physical examination, liver enzymes, bilirubin, albumin, clotting tests, imaging, and other appropriate investigations. Some people with liver disease may have completely different BUN patterns depending on hydration and kidney function. Therefore, the ratio can contribute to clinical reasoning but should never replace dedicated liver testing.
Excessive fluid intake or certain conditions causing increased body water can sometimes reduce BUN concentration through dilution. This may make the BUN creatinine ratio appear lower even when urea production itself has not changed substantially. Fluid balance is complex because both dehydration and overhydration can arise from many medical and nonmedical situations. Doctors may examine sodium levels, body weight changes, swelling, blood pressure, urine concentration, and other findings when evaluating possible fluid imbalance. Simply drinking additional water to change a laboratory result is not an appropriate strategy without medical guidance. Excessive water consumption can itself become dangerous if it disrupts sodium balance.
A relatively elevated creatinine can also lower the ratio. Creatinine may increase because of decreased kidney filtration, substantial muscle mass, vigorous physical activity, muscle injury, or certain medications and supplements. For example, intense resistance training shortly before testing may temporarily influence creatinine in some individuals. People who regularly consume creatine supplements may also have differences in creatinine measurements, although the significance varies considerably. Severe muscle damage can cause much larger changes and may involve additional laboratory abnormalities. Because creatinine is affected by factors beyond kidney function, physicians evaluate the entire clinical picture before interpreting a low ratio as evidence of a particular condition.
Many mildly low ratios are discovered incidentally in people who feel completely well. When BUN, creatinine, estimated glomerular filtration rate, electrolytes, and other relevant results are reassuring, a small deviation may not have major clinical importance. A doctor may simply compare the result with previous tests or repeat the laboratory panel later. More investigation may be appropriate when the abnormality persists, changes substantially, or occurs alongside symptoms or additional abnormal blood tests. Nutrition, medications, liver health, muscle injury, and hydration may all need consideration. The important point is that a low BUN creatinine ratio is a laboratory pattern requiring interpretation rather than a disease with one specific cause.
BUN Creatinine Ratio and Kidney Function
The kidneys continuously filter blood, removing metabolic waste while maintaining fluid, electrolyte, and acid-base balance. Both BUN and creatinine are commonly measured because their concentrations can change when kidney filtration becomes impaired. Creatinine has an especially important role in estimating kidney function because it is used in formulas that calculate the estimated glomerular filtration rate, often abbreviated as eGFR. However, creatinine is not a perfect marker because its production depends partly on muscle mass. BUN is also imperfect because hydration, protein intake, liver function, and other factors influence it substantially. Looking at multiple measurements therefore gives clinicians a better understanding than relying on either marker alone.
When kidney filtration declines, creatinine may accumulate in the blood because the kidneys are removing less of it. BUN can also rise because urea is not being cleared as efficiently. If both values rise proportionately, the BUN creatinine ratio may remain within a commonly accepted range despite impaired kidney function. This illustrates why a normal ratio cannot rule out kidney disease. The creatinine level and eGFR generally provide more direct information about filtration than the ratio itself. Urine testing can add further information by detecting albumin, blood, protein, inflammatory cells, or other abnormalities that may help identify kidney damage.
A sudden increase in creatinine is particularly important because it may represent acute kidney injury, especially when accompanied by changes in urine output or other laboratory abnormalities. Acute kidney injury can occur because of severe dehydration, infection, reduced blood pressure, medication effects, urinary obstruction, or direct damage to kidney tissue. The BUN creatinine ratio may sometimes help clinicians distinguish possible categories of kidney problems, but modern assessment does not rely on the ratio alone. Changes in creatinine over time, fluid status, medication history, urine studies, and imaging may all be necessary. Rapidly changing kidney results should receive timely medical evaluation because early recognition can influence treatment and recovery.
Chronic kidney disease develops over a longer period and is generally identified through persistent evidence of reduced kidney function or kidney damage. Diabetes, high blood pressure, cardiovascular disease, inherited disorders, and several inflammatory conditions can increase the risk of chronic kidney problems. In these situations, clinicians often monitor eGFR and urine albumin in addition to blood pressure and metabolic measurements. BUN may rise as kidney disease progresses, but it is not used alone to determine the stage of chronic kidney disease. Likewise, the BUN creatinine ratio cannot establish a stage or prognosis. Long-term trends and multiple markers provide much more useful information.
People concerned about kidney health should avoid trying to diagnose themselves using the BUN creatinine ratio alone. A laboratory number may look alarming online while being understandable in the context of temporary dehydration, muscle mass, diet, or medication use. Conversely, a ratio within the normal range does not guarantee that kidney function is ideal. Reviewing the creatinine level, eGFR, urine albumin measurement, blood pressure, and medical history provides a more complete evaluation. Individuals with diabetes, hypertension, cardiovascular disease, or a family history of kidney disease may need periodic kidney screening. The appropriate testing schedule depends on personal risk factors and should be discussed with a healthcare professional.
Factors That Can Affect BUN and Creatinine Results
Hydration is among the most important short-term influences on BUN measurements. Losing significant fluids through vomiting, diarrhea, fever, sweating, or insufficient drinking can increase BUN and sometimes creatinine as well. The effect may be more noticeable in older adults, people taking diuretics, and individuals experiencing acute illness. Drinking excessive amounts of fluid can move the numbers in the opposite direction and potentially dilute BUN. Normal day-to-day differences in fluid intake can also cause smaller variations. Because hydration can affect laboratory interpretation, telling your healthcare provider about recent illness or unusual fluid losses can be helpful when reviewing unexpected results.
Diet is another variable that can affect BUN. Protein from meat, fish, eggs, dairy foods, legumes, and other sources ultimately contributes to nitrogen waste after metabolism. A particularly high-protein diet may therefore increase BUN in some people, while prolonged low protein intake can lower it. This does not mean dietary protein should automatically be restricted when BUN is elevated. Protein needs vary according to age, overall health, activity level, nutritional status, and kidney function. Unnecessary protein restriction can create nutritional problems, particularly for older adults or individuals already at risk for muscle loss. Any significant dietary adjustment related to kidney concerns should be guided by appropriate clinical advice.
Muscle mass has a particularly important influence on creatinine. People with greater muscle mass often produce more creatinine and may naturally have somewhat higher levels than people with less muscle tissue. Conversely, older adults or individuals with significant muscle loss may produce relatively little creatinine, which can complicate estimates of kidney function. Strenuous exercise can sometimes temporarily increase creatinine, especially after unusually intense activity. Serious muscle injury may produce much larger changes and can potentially threaten kidney function. These differences demonstrate why a creatinine result should be interpreted according to the person’s physical characteristics, health history, activity, and other laboratory findings.
Medications and supplements can influence kidney-related blood tests through several mechanisms. Some medicines affect kidney blood flow, while others alter creatinine secretion or can contribute to kidney injury in susceptible people. Diuretics may influence hydration status, and corticosteroids can affect protein metabolism under certain circumstances. Creatine supplements may alter creatinine measurements in some individuals because creatine is related to creatinine production. People should tell their healthcare professional about prescription medications, nonprescription drugs, vitamins, sports supplements, and herbal products when abnormal laboratory results are being evaluated. Medications should not be stopped simply because of an online interpretation of a BUN creatinine ratio unless a qualified clinician recommends doing so.
Age, pregnancy, illness, nutrition, body composition, and chronic health conditions can further influence BUN or creatinine measurements. Pregnancy changes blood volume and kidney filtration, so laboratory values may differ from typical nonpregnant adult ranges. Severe infections or other major illnesses can increase protein breakdown and affect both kidney blood flow and metabolic waste production. Cardiovascular conditions can influence circulation to the kidneys, while liver disease can alter urea production. Malnutrition may lower BUN and reduce muscle mass, potentially affecting creatinine simultaneously. Because so many variables influence these tests, clinicians place greater emphasis on patterns, associated findings, and changes over time than on any isolated number.
How Doctors Interpret an Abnormal BUN Creatinine Ratio
Interpreting an abnormal ratio typically begins with looking at BUN and creatinine separately. A ratio can be high because BUN increased, because creatinine decreased, or because both changed in different proportions. Likewise, a low ratio might reflect decreased BUN, elevated creatinine, or a combination of both. These distinctions matter because each pattern has different potential explanations. The clinician then considers whether the values changed from previous tests and whether the person has symptoms suggesting dehydration, infection, bleeding, urinary problems, or another condition. This step-by-step approach prevents the mathematical ratio from being mistaken for a standalone diagnosis.
The estimated glomerular filtration rate is frequently reviewed alongside creatinine because it provides an estimate of how effectively the kidneys are filtering blood. eGFR calculations generally incorporate serum creatinine with demographic information such as age and sex, depending on the equation used. Current clinical practice has moved away from including race as an adjustment in widely adopted creatinine-based eGFR equations. Even eGFR has limitations, particularly when muscle mass is unusually high or low. In selected situations, clinicians may consider another filtration marker such as cystatin C. Combining appropriate measurements can provide a more reliable assessment when standard creatinine-based estimates appear inconsistent with the clinical picture.
Urine tests often provide information that blood measurements cannot. A urine albumin-to-creatinine ratio can detect small amounts of albumin leaking into urine, which may indicate kidney damage even when blood creatinine appears relatively normal. A routine urinalysis can identify blood, protein, glucose, inflammatory cells, concentration abnormalities, and other findings. Depending on symptoms, clinicians may also assess urine sodium or other specialized measurements. These tests can help distinguish different categories of kidney and urinary problems. Therefore, someone worried about kidney disease should not assume that the blood BUN creatinine ratio represents a complete kidney evaluation.
Other laboratory measurements help place the ratio into context. Sodium and potassium may reveal fluid or electrolyte disturbances, while bicarbonate provides information about acid-base balance. Liver function tests can be helpful when unusually low urea production is suspected. A complete blood count may be ordered when bleeding, anemia, or infection is possible. Creatine kinase testing may be appropriate when severe muscle injury is suspected. The exact combination of tests depends on symptoms and clinical circumstances rather than following one universal protocol. A clinician’s interpretation usually involves combining these measurements with blood pressure, physical examination findings, medication history, dietary information, and previous laboratory trends.
Sometimes the most appropriate next step is simply repeating the blood test. Mild abnormalities caused by temporary dehydration, recent illness, intense exercise, or dietary changes may improve once the short-term factor resolves. A repeat result helps show whether the abnormality was temporary or persistent. More substantial abnormalities, worsening creatinine, significant electrolyte disturbances, or concerning symptoms generally require faster evaluation rather than routine retesting. Imaging such as a kidney ultrasound may be needed when urinary obstruction or structural abnormalities are suspected. Ultimately, the appropriate response depends not on whether the ratio is technically high or low, but on why it changed and whether kidney function or overall health is being affected.
What to Do If Your BUN Creatinine Ratio Is Abnormal
The first step after seeing an abnormal BUN creatinine ratio is to avoid assuming the worst. Laboratory reports often flag values that fall slightly outside statistical reference intervals, but a flagged measurement is not automatically evidence of serious disease. Review whether BUN and creatinine are individually normal and look at the reported eGFR if one is provided. It can also be useful to compare the results with previous laboratory tests. A small stable difference over several years may have different significance than a large change over several days. Your healthcare professional can determine whether the finding fits your normal pattern or requires additional evaluation.
Consider what was happening around the time of the blood test. Recent vomiting, diarrhea, fever, heavy sweating, fasting, major dietary changes, intense exercise, or inadequate fluid intake can potentially influence kidney-related measurements. Medications and supplements may also affect the results, so prepare an accurate list of everything you use regularly or recently started. Do not deliberately drink excessive water before repeat testing unless your healthcare provider specifically instructs you to do so. Overhydration can distort laboratory measurements and, in extreme situations, cause dangerous electrolyte abnormalities. Normal hydration and following the laboratory’s preparation instructions usually provide the most useful testing conditions.
If dehydration is considered likely and there is no medical reason to restrict fluids, restoring ordinary fluid intake may be part of the medical advice you receive. However, people with heart failure, advanced kidney disease, certain electrolyte problems, or other conditions may have specific fluid limits. This is why generic advice to simply drink large amounts of water is not appropriate for everyone. Persistent vomiting or diarrhea can also cause electrolyte losses that water alone may not adequately address. Severe dehydration may require urgent medical treatment. The safest approach is to match hydration recommendations to the person’s symptoms and existing medical conditions rather than responding only to the laboratory ratio.
Follow-up becomes particularly important when creatinine is rising, eGFR is declining, or urine tests show blood or protein. A healthcare professional may repeat laboratory testing, review medications, evaluate blood pressure, request urine studies, or recommend additional investigation. People with diabetes or high blood pressure may require closer kidney monitoring because these conditions are important contributors to chronic kidney disease. Early identification of kidney problems can allow underlying risk factors to be addressed before substantial loss of function occurs. However, kidney-related treatment depends on the specific cause rather than the BUN creatinine ratio alone. There is no single medication or diet that is appropriate for every abnormal ratio.
Avoid dramatically changing your diet, stopping medication, starting supplements, or following a kidney detox program based solely on one test result. Some supplements and unregulated remedies can actually worsen kidney function or interact with prescription medicines. Protein restriction can also be inappropriate when it is not medically necessary, particularly for people who need adequate nutrition to maintain muscle mass. Instead, discuss persistent abnormalities with a qualified healthcare professional who can consider your full health history. Bringing previous laboratory results can be especially helpful because trends provide important context. The objective is not merely to make the ratio appear normal, but to understand whether there is an underlying issue that needs attention.
When Should You Seek Medical Care?
Most isolated mild abnormalities in the BUN creatinine ratio are not medical emergencies. However, the importance of the result changes when it occurs alongside significant symptoms or rapidly worsening laboratory findings. Contact a healthcare professional when abnormal kidney-related results persist, are considerably different from previous measurements, or occur with unexplained fatigue, swelling, changes in urination, nausea, or other ongoing symptoms. People with existing kidney disease, heart disease, diabetes, or hypertension may need earlier follow-up because their baseline risk is higher. A clinician can determine whether repeating laboratory testing is sufficient or whether more immediate evaluation is necessary.
A major reduction in urine production deserves prompt attention, particularly when it occurs with swelling, shortness of breath, weakness, confusion, or significant illness. Producing very little urine can occur when blood flow to the kidneys is severely reduced, when the kidneys are acutely injured, or when urine flow is obstructed. These situations cannot be distinguished simply by calculating the BUN creatinine ratio. Blood testing, urine testing, physical examination, and sometimes imaging may be necessary. Suddenly worsening kidney function can also disrupt potassium, acid-base balance, and fluid levels. Because these complications can become serious, rapidly changing symptoms should not be managed through home interpretation of laboratory results.
Signs of substantial dehydration also deserve attention. Persistent vomiting or diarrhea, inability to keep fluids down, severe dizziness, fainting, confusion, rapid heartbeat, or extreme weakness may indicate that fluid losses have become significant. Older adults and people taking certain medications may be particularly vulnerable to complications from dehydration. A high BUN creatinine ratio might accompany this situation, but symptoms and overall condition are more important than the ratio itself. Severe dehydration can reduce kidney blood flow and contribute to acute kidney injury if it continues. Medical treatment may be needed to restore fluids and electrolytes safely.
Possible gastrointestinal bleeding should be treated seriously regardless of the BUN creatinine ratio. Black, sticky or tar-like stools, vomiting blood, vomiting material that resembles coffee grounds, fainting, severe dizziness, or substantial weakness can indicate internal bleeding. An increased BUN relative to creatinine may sometimes appear with upper gastrointestinal bleeding, but laboratory interpretation should never delay urgent evaluation of these symptoms. Significant bleeding can cause dangerous decreases in blood volume and blood pressure. Depending on severity, emergency treatment may be necessary. Anyone experiencing symptoms suggesting major internal bleeding should seek prompt medical care rather than waiting for another blood test.
Ultimately, an abnormal BUN creatinine ratio becomes meaningful only when considered within the broader health picture. Mild changes without symptoms often have relatively simple explanations, whereas major changes combined with abnormal creatinine, falling eGFR, electrolyte problems, reduced urine output, or systemic illness deserve closer attention. The ratio is useful because it can provide clues about hydration, protein metabolism, circulation, and kidney-related physiology. It is not designed to tell you exactly what disease you have. Understanding that distinction can reduce unnecessary worry while still encouraging appropriate medical follow-up. When results are unexpected, discussing them with the clinician who ordered the test remains the best next step.
Frequently Asked Questions
What is considered a good BUN creatinine ratio?
A BUN creatinine ratio of roughly 10:1 to 20:1 is commonly considered within the expected adult range when both measurements are reported in mg/dL. Laboratory reference intervals vary, so the range printed on your own test report should take priority.
Is a high BUN creatinine ratio always a kidney problem?
No. A high ratio can occur with dehydration, reduced blood flow to the kidneys, gastrointestinal bleeding, high protein intake, increased protein breakdown, and several other situations. Kidney function should be assessed using the individual creatinine value, eGFR, urine testing, symptoms, and medical history rather than the ratio alone.
Can dehydration increase the BUN creatinine ratio?
Yes. Dehydration can reduce blood flow through the kidneys and cause BUN to rise disproportionately compared with creatinine. The degree of change varies, and significant dehydration should be evaluated based on symptoms, physical findings, electrolytes, and kidney function rather than the ratio alone.
What does a low BUN creatinine ratio indicate?
A low ratio may occur with low protein intake, reduced urea production associated with significant liver dysfunction, increased body water, increased creatinine production, or other circumstances. Mild isolated reductions may not be clinically important, especially when the remaining kidney and metabolic tests are normal.
Which is more important, creatinine or the BUN creatinine ratio?
Creatinine and the estimated glomerular filtration rate are generally more directly useful for assessing kidney filtration than the BUN creatinine ratio alone. However, clinicians often evaluate BUN, creatinine, eGFR, urine albumin, electrolytes, symptoms, medications, hydration status, and trends together to understand kidney health accurately.


